Introduction
In clinical practice, we often encounter scars accompanied by pigmentation complications.
In fact, most scars exhibit significant color changes, primarily manifesting in two forms: 1. Hyperpigmentation, where the scarred skin darkens. 2. Hypopigmentation or even depigmentation may also occur, resulting in lighter or whitened skin.
How do these occur? And how should they be addressed and treated? Today, let’s explore this together.

Why Does Depigmentation Occur?
Depigmentation is divided into congenital and acquired types. Scarring is the main cause of acquired depigmentation, with common causes including mechanical trauma, burns, chemical damage, inflammatory injuries such as acne, and iatrogenic injuries (including surgery, laser treatment, and radiation damage). The core cause of depigmentation due to scarring stems from two major pathological changes: a decrease in the number of melanocytes and functional impairment.
First, there is a decrease in the absolute number of melanocytes. During the wound healing phase, physical damage occurs to skin appendages rich in melanocytes, such as hair follicles. Simultaneously, the inflammatory response during the repair period induces melanocyte apoptosis, directly leading to a reduction in cell number. Mature scar tissue, primarily composed of fibroblasts and secreted fibrin, lacks melanocytes and related skin appendages, making it unable to replenish melanocyte reserves.
Second, there is functional impairment mediated by the inflammatory immune microenvironment. Inflammation-mediated indirect damage is key to the occurrence of depigmentation. Excessive tissue fibrosis leads to local vascular insufficiency and hypoxia, coupled with the massive infiltration of inflammatory factors and immune cells, creating a persistent inflammatory microenvironment at the scar site, exhibiting a distinct stage effect: In the early stages of inflammation, inflammatory mediators increase tyrosinase activity, resulting in hyperactive melanocytes and post-inflammatory hyperpigmentation; as inflammation worsens, excessive cytokines and reactive oxygen species disrupt the metabolism and activity of melanocytes, causing functional inhibition or even permanent damage, ultimately leading to their clearance by macrophages during tissue remodeling, progressing to hypopigmentation or even complete depigmentation.
In short, the temporal changes in scar development from hyperpigmentation to depigmentation are essentially external manifestations of different degrees and stages of skin inflammation.

Treatment Theory of Scar Depigmentation
Treatment of scar depigmentation should follow the principle of “surgery as the primary approach, combined with comprehensive enhancement, and sequential intervention.” Addressing the common issue of simultaneous hyperpigmentation and hypopigmentation, and considering that hypopigmentation is relatively stable while hyperpigmentation is easily affected by inflammation, and that hyperpigmentation treatment has clear targets and more methods, relevant research suggests that the overall treatment strategy should prioritize treating hypopigmentation. Once the skin tone has stabilized, residual hyperpigmentation can then be addressed to achieve a natural and even skin tone.
Currently, various medications for hypopigmentation primarily focus on protecting, inducing, and activating melanocyte function. Therefore, their effectiveness depends on the condition of remaining cells and the timing of treatment. However, significant hypopigmentation symptoms often appear gradually after the inflammatory phase, easily missing the optimal window for drug intervention. Furthermore, the absolute reduction in melanocyte count is common, making them insensitive to simple drug treatment and only suitable for long-term adjunctive therapy.
With the development of photoelectric technology, photoelectric devices are increasingly used in scar treatment. Besides improving scar texture and smoothness, improving scar color is also one of its main clinical effects. Currently, photoelectric therapy can be used as a localized method to increase melanin production and correct depigmentation.
Treatment Methods for Scar Depigmentation
1. IPL + E-light Device.
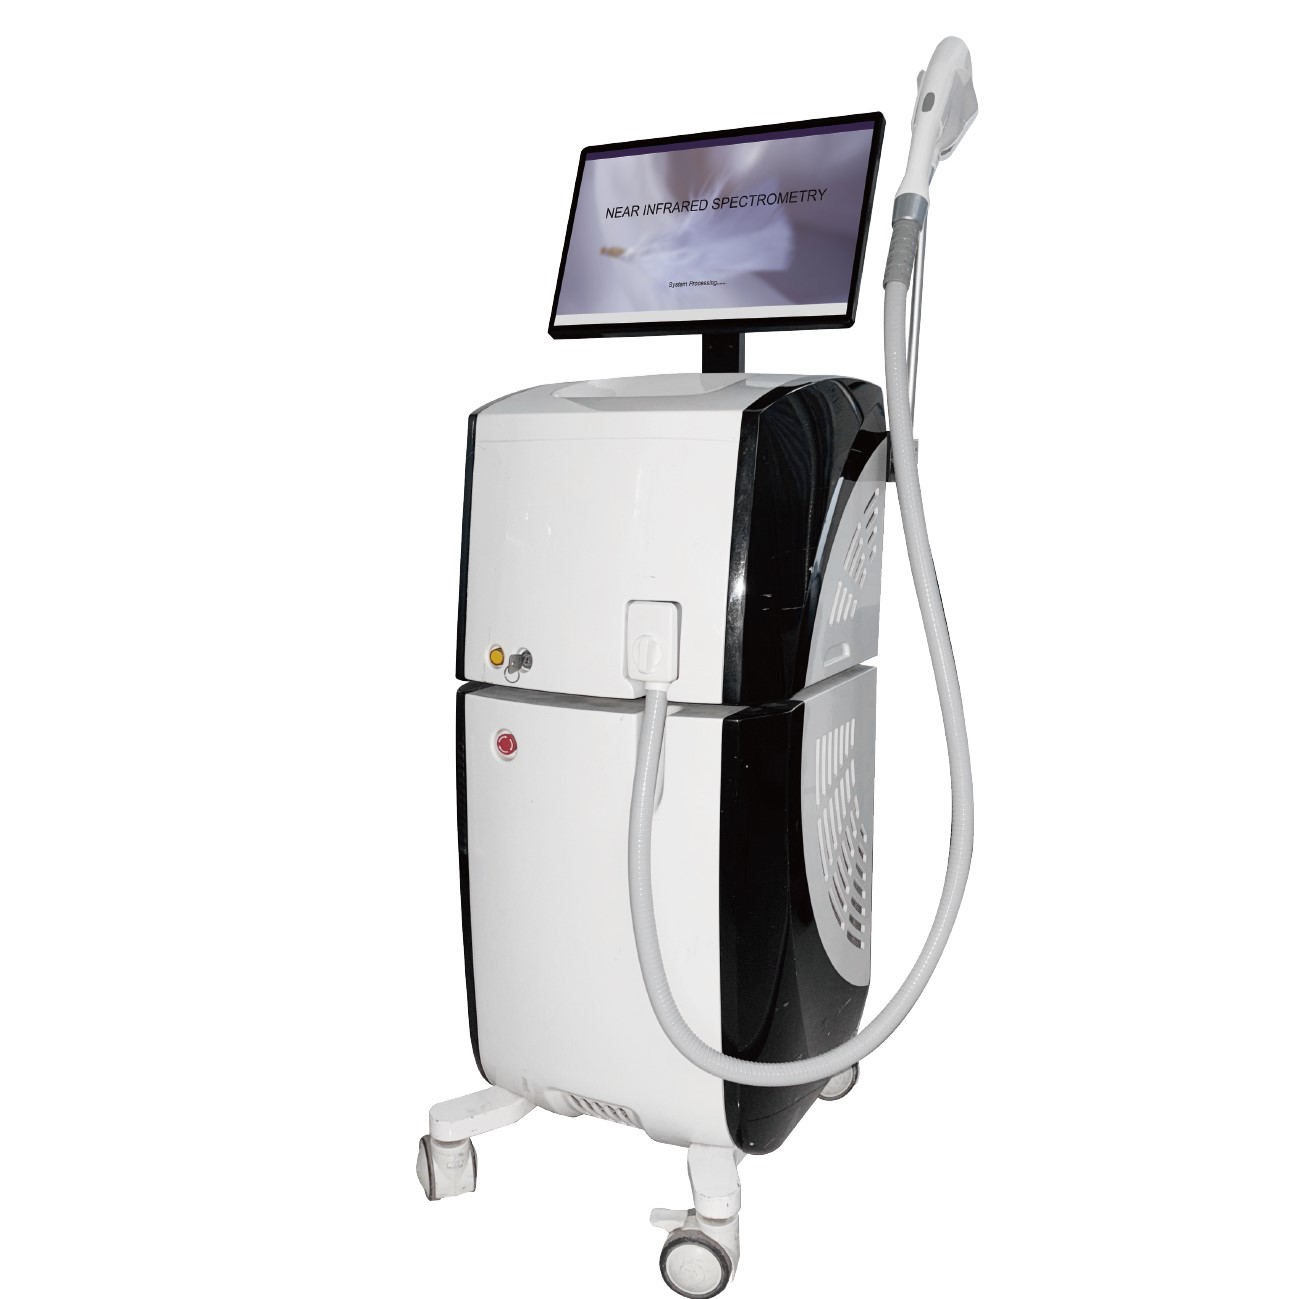
We can choose to treat with an IPL+E-light device. Intense pulsed light combined with radiofrequency sequential therapy (E-light) is also used to treat pigmentation abnormalities caused by scarring. The key to E-light treatment for depigmentation is to achieve an even skin tone; therefore, the wavelength of IPL (530, 560, 580, 630, or 755nm) must be adjusted according to the patient’s skin tone. When treating scar depigmentation, the energy range of E-light is 38-42J, and the energy of radiofrequency is 8-10J.

2. Fractional Laser Treatment
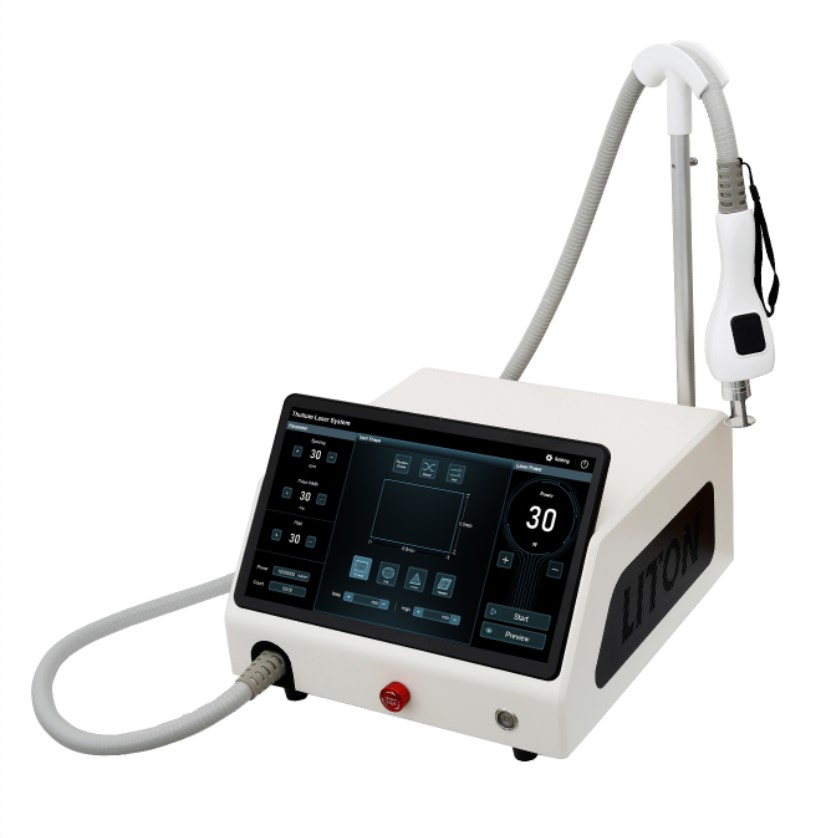
The mechanism by which fractional lasers, such as CO₂ fractional laser and 1927nm/1550nm Thulium-Erbium Laser, improve scar pigmentation may be related to regulating the secretion of inflammatory factors, improving the skin microenvironment, and promoting the proliferation and interaction of melanocytes and keratinocytes.
Related studies have found that CO₂ fractional laser treatment, starting three months after injury and performed at one-month intervals, yields better results for scar pigmentation. Other studies have shown that using the artificial fractional mode of CO₂ fractional lasers achieved a 90.7% repigmentation rate in scar pigmentation.
During treatment, high-density, low-energy fractional lasers can be used to treat vitiligo, causing minor epidermal damage and forming punctate eschars. After eschar removal, combined with light irradiation, the tissue experiences pigmentation-induced hemorrhage (PIH), thereby improving scar-related depigmentation.
Overall, fractional lasers have significant advantages in treating scar pigmentation, especially when combined with topical medications after opening skin channels, resulting in better repigmentation. Furthermore, the overall benefit of non-ablative fractional lasers is superior to that of ablative fractional lasers.


3. Ultraviolet Radiation (UVA/UVB)
Narrow-band UVB (308nm) or UVA can directly stimulate the proliferation and migration of residual melanocytes, activate tyrosinase activity to produce melanin granules, thereby causing scar depigmentation and repigmentation.
4. 308nm Excimer Laser
We evaluated the efficacy of 308nm excimer laser in hypoplastic scars. After 9 treatments, visual assessment revealed a pigmentation correction rate of up to 70%, but pigmentation levels gradually decreased to baseline over 6 months, indicating a high recurrence rate for hypoplastic scars.
Frequently Asked Questions
Q1: How to avoid depigmentation during laser treatment?
1. Preoperative Assessment: Assess the patient’s skin color (Fitzpatrick classification), history of pigmentation disorders, previous laser treatment history, and desired outcome. Individuals with darker skin types (Fitzpatrick IV-VI) have higher sensitivity to energy and inflammation, requiring a more conservative approach.
2. Appropriate Equipment and Parameter Selection: Use parameters that are well-matched to the indications and proven safe. For darker skin, reduce intensity and treatment density (reduce energy, density or number of treatments, increase cooling, extend pulse intervals, etc.).
3. Good Intraoperative/Postoperative Care: Provide adequate cooling and anti-inflammatory treatment. If necessary, administer short-term topical corticosteroids, but avoid long-term use to prevent complications. Strict sun protection is essential, as UV radiation may worsen pigmentation disorders. Instruct postoperative care to prevent secondary damage.
4. Risk Information and Follow-up: Communicate potential pigmentation complications (including depigmentation and hyperpigmentation) to the patient preoperatively and arrange follow-up for early detection and management.
Q2: Can I have laser treatment again after depigmentation?
Generally, areas that have already depigmented should not be immediately treated again with high-energy or similar pigment-targeting lasers. The goals and methods of re-treatment must be approached with extreme caution, adhering to the following principles:
1. Waiting and assessment period: Before planning re-treatment, confirm that the pigmentation is stable and observe for several months, typically at least 3–6 months or longer, depending on the specific situation.
2. Test point treatment: Before re-treatment, perform a low-energy test on a concealed area in front of the ear or jawline to observe the skin reaction (for at least several weeks) and check for further depigmentation or hyperpigmentation.
3. Choose a gentle treatment plan: If re-treatment is necessary, prioritize low-energy, low-density, non-ablative, or superficial devices, extending treatment intervals. Exercise extreme caution or avoid deep or highly destructive devices or treatment parameters (such as full-thickness ablation or dermabrasion).
4. Combined pigment-promoting therapy: If necessary, topical corticosteroids or pigment-promoting drugs may be considered before and after treatment to promote repigmentation and reduce risks.
Q3: What are some common treatments for depigmentation?
1. Laser Treatment
Primarily includes ultraviolet light therapy, 308nm excimer laser, and CO2 fractional laser, often requiring multiple treatments. Generally speaking, for truly significant depigmentation, phototherapy has limited effectiveness, and often no effect at all.
2. Epidermal Grafting
This is one of the most commonly used methods, especially suitable for smooth-surfaced depigmentation. Unlike skin grafting, epidermal grafting only transplants the epidermis, requiring no sutures, and leaving no scar at the harvest site.
3. Excision and Suture
For depigmentation scars that can be sutured after excision without causing traction deformities to surrounding tissues and organs, excision and suturing is the most effective treatment, often providing the greatest improvement.
4. Microcomposite Tissue Grafting (MCGT)
Normal composite tissue particles are harvested from a concealed area using a trephine and transplanted to the depigmented area. This method is particularly suitable for treating linear depigmentation scars; after the tissue particles survive, combined with laser treatment, significant improvement can be achieved.
5. Pigmentation Tattooing
The principle of pigmentation tattooing is exactly the same as that of permanent tattooing, except that tattooing aims to highlight “difference,” while pigmentation tattooing aims to eliminate “difference.” Pigmentation tattooing is suitable for smooth, depigmented scars. For uneven scars, they need to be smoothed first before pigmentation tattooing. Furthermore, most pigmentation tattoos currently available are “semi-permanent,” not permanent.
6. Others
Such as microneedling and traditional Chinese medicine, there are also many successful cases.
Despite the many treatment methods available, depigmentation or hypoplasia scars remain a clinical challenge. Generally speaking, there is still a lack of widely applicable and highly effective methods.
High-quality Depigmentation Therapy machine
Liton Laser, established in 2001, is a manufacturer of cosmetic equipment and offers a variety of depigmentation treatment machines.
For different degrees of pigmentation loss, we can recommend different types of machines, including CO2 fractional lasers, 1927nm + 1550nm thulium-erbium fractional lasers, and E-light + IPL devices.
If you need a pigmentation removal treatment device, please feel free to contact us. We not only sell fractional lasers and intense pulsed light (IPL), but also recommend MBS Tech products if you require excimer lasers or other physiotherapy/aesthetic equipment.
Regardless of your country of origin, our machines will be configured with the appropriate specifications and voltage to ensure proper operation. Core components are sourced from leading market brands. The laser bar is from the USA, the drive unit is from Germany, and the Electrical Transformer is from CHBEB.
Conclusion
1. The key and challenge in effectively improving depigmentation in scar tissue lies in inducing a response from melanocytes in the scar tissue and preventing the formation of new pigmentation problems, reducing the formation of new scars, and lowering the probability of postoperative complications such as infection and pain. It also requires balancing risks and benefits when choosing a treatment plan.
2. Fractional laser or fractional laser combined with medication results in small wounds, a low risk of infection, and definite efficacy. However, the recurrence rate of depigmentation is high, and its stability and durability require further investigation.